
Surrogacy success rates can range widely depending on what is being measured — from an embryo transfer to a clinically confirmed pregnancy or a live birth. Age of the egg source, embryo quality, genetic testing, and the surrogate’s health history can all affect the outcome.
A surrogate mother success rate is best understood in terms of the outcome being measured. For gestational surrogacy, published clinical pregnancy rates are about 51.8% with intended-mother eggs and 69.8% with donor eggs.
- Gestational surrogacy success rates typically range from 65–95%, depending on the type of surrogacy and whether success is measured per embryo transfer or after pregnancy is confirmed.
- Gestational surrogacy clinical pregnancy rates are reported at about 51.8% with intended-mother eggs and 69.8% with donor eggs.
- Egg age, embryo quality, surrogate screening, and clinical factors can substantially change outcomes.
- Reliable comparative success-rate data for traditional surrogacy remain limited.
- A reported 95% success rate should always be checked for its definition and stage of treatment.
- A failed first embryo transfer does not determine the cumulative chance of success across subsequent attempts.

What Is a Surrogate Mother Success Rate?
A surrogate mother success rate refers to the percentage of surrogacy cycles that achieve a specific outcome, such as a clinical pregnancy or live birth. For gestational surrogacy, published clinical pregnancy rates are about 51.8% when using the intended mother’s eggs and 69.8% when using donor eggs.
These figures measure clinical pregnancy, not live birth after the first embryo transfer. The reported rate therefore needs to be understood alongside the outcome and treatment stage being measured.

How Are Surrogacy Success Rates Measured?
Surrogacy success rates can refer to different outcomes, so the percentage alone does not tell the full story. The most common measures are:
- Pregnancy rate: The percentage of embryo transfers that result in pregnancy.
- Clinical pregnancy rate: The percentage of transfers that result in a pregnancy confirmed by ultrasound, typically showing a gestational sac and/or fetal heartbeat.
- Live birth rate: The percentage of cycles or embryo transfers that result in a live-born baby.
Clinics may also report rates using different denominators, such as per IVF cycle started, per embryo transfer, or per patient. The patient group can also affect the figure, including factors such as egg-source age, embryo quality, genetic testing, and whether donor eggs were used.
For this reason, a reported success rate should always be read together with its outcome, denominator, patient group, sample size, and reporting period. A 95% clinical pregnancy rate, for example, cannot be directly compared with a 60% live birth rate per embryo transfer because they measure different outcomes.

How to Read a Surrogacy Success Rate
When a clinic or agency reports a 90% or 95% success rate, the key question is: 95% of what?
Look for four details:
- Outcome: pregnancy, clinical pregnancy, or live birth.
- Denominator: embryo transfer, IVF cycle, or treatment after pregnancy has already been confirmed.
- Patient group: age of the egg source, donor eggs, embryo quality, and other characteristics included in the figure.
- Sample size and period: how many cases are represented and when they occurred.
For example, a 95% success rate after pregnancy has already been confirmed should not be compared directly with a 60% live birth rate per embryo transfer. They measure different stages of the journey.
Average Surrogacy Success Rates Worldwide
Because gestational surrogacy relies on IVF technology, most publicly available data on success rates actually comes from national IVF and ART (assisted reproductive technology) reporting systems — not from surrogacy agencies themselves, which aren’t required to publish their outcomes the way clinics are. That’s worth keeping in mind as you look at the numbers below.
Success Rates by Live Birth
In the United States, roughly 435,426 ART cycles were performed across 457 reporting clinics in 2022, resulting in about 94,039 live births and 98,289 live-born infants. That works out to a live birth rate of about 22% per cycle started — though that number climbs significantly when you break it down by age and embryo type, which is why averages alone can be misleading.
Success Rates by Embryo Transfer
Transfer-based success rates tend to look higher than cycle-based rates, since they only count cycles that made it far enough to transfer an embryo. Clinics have also shifted their approach in ways that affect these numbers — single embryo transfers were used in 70.7% of cycles in 2021, rising to 73.9% in 2022, largely to reduce the risks that come with twin or multiple pregnancies (SART CORS Online).
Because transfer-based figures only include cycles that reached embryo transfer, they should not be compared directly with rates calculated from every cycle started.
Success Rates by Age
Age remains one of the biggest predictors of success, whether the eggs come from the intended mother or an egg donor. According to national SART data, live birth rates per intended egg retrieval were 43.1% for patients under 35, dropping to 31% for those 35 to 37, and 19% for those 38 to 40 — falling to just 3.2% for patients over 42 (SART CORS Online).
That steep decline is one of the main reasons donor eggs are so often recommended once intended mothers pass their late 30s — and why egg donor age, not the intended mother’s age alone, plays such a large role in surrogacy outcomes specifically.
| Country | Average Success Rate | Average Cost | Legal Status |
|---|---|---|---|
| Iran | 95%* | $18K–30K | Legal |
| USA | 85–90% | $100K+ | State-dependent |
| Ukraine | 80–85% | $30K–50K | Legal |
| Georgia | 75–80% | $25K–40K | Legal |
*The 95% success rate for Iran refers to pregnancies that have already been clinically confirmed, rather than the success rate per first embryo transfer.
Gestational vs. Traditional Surrogacy Success Rates
Not all surrogacy arrangements work the same way biologically, and that difference has a direct impact on success rates. The vast majority of surrogacy journeys today are gestational, but it’s worth understanding both paths — and why one has become the clear industry standard.
Gestational Surrogacy Success Rates
In gestational surrogacy, the surrogate carries an embryo created through IVF using the intended parents’ egg and sperm, or donor eggs and/or sperm. She has no genetic connection to the child, since the embryo isn’t made from her own egg (PubMed Central).
This distinction turns out to matter for outcomes, not just biology. According to data from the American Society for Reproductive Medicine, gestational carriers using the intended mother’s own eggs achieve a clinical pregnancy about 51.8% of the time, and that rises to roughly 69.8% when donor eggs are used. Both figures run noticeably higher than pregnancies carried by the intended mother herself using the same egg source — a gap researchers attribute partly to gestational carriers typically having a proven, healthy uterine history.
Gestational surrogacy has also become the overwhelming norm. Gestational carriers now account for about 5% of all embryo transfers in the U.S., a sharp rise from roughly 2.2% just over a decade earlier — a trend that reflects how far more predictable and legally straightforward this path has become for intended parents and surrogates alike (Women & Infants Fertility Center).
Traditional Surrogacy Success Rates
Traditional surrogacy works differently: the surrogate uses her own egg, which is fertilized with the intended father’s or a donor’s sperm. That means she’s genetically related to the baby she carries — a distinction that carries emotional and legal weight beyond just the medical process.
Reliable success rate data for traditional surrogacy is hard to come by, and that’s not an oversight — it’s because so few clinics and agencies offer it anymore. Data on traditional surrogacy outcomes remains limited largely because so few intended parents and surrogates pursue this arrangement today, and the genetic link often complicates parentage rights after birth.
That said, the limited research available suggests outcomes tend to run lower than gestational arrangements. One reason: many traditional surrogacy conceptions happen through simpler methods like at-home insemination rather than clinically monitored IVF cycles, which naturally introduces more variability into the outcome.
For most intended parents today, gestational surrogacy isn’t just the more common choice — it’s generally the one associated with more predictable, higher success rates and a clearer legal path to parenthood.
Key Factors That Determine Surrogacy Success Rates
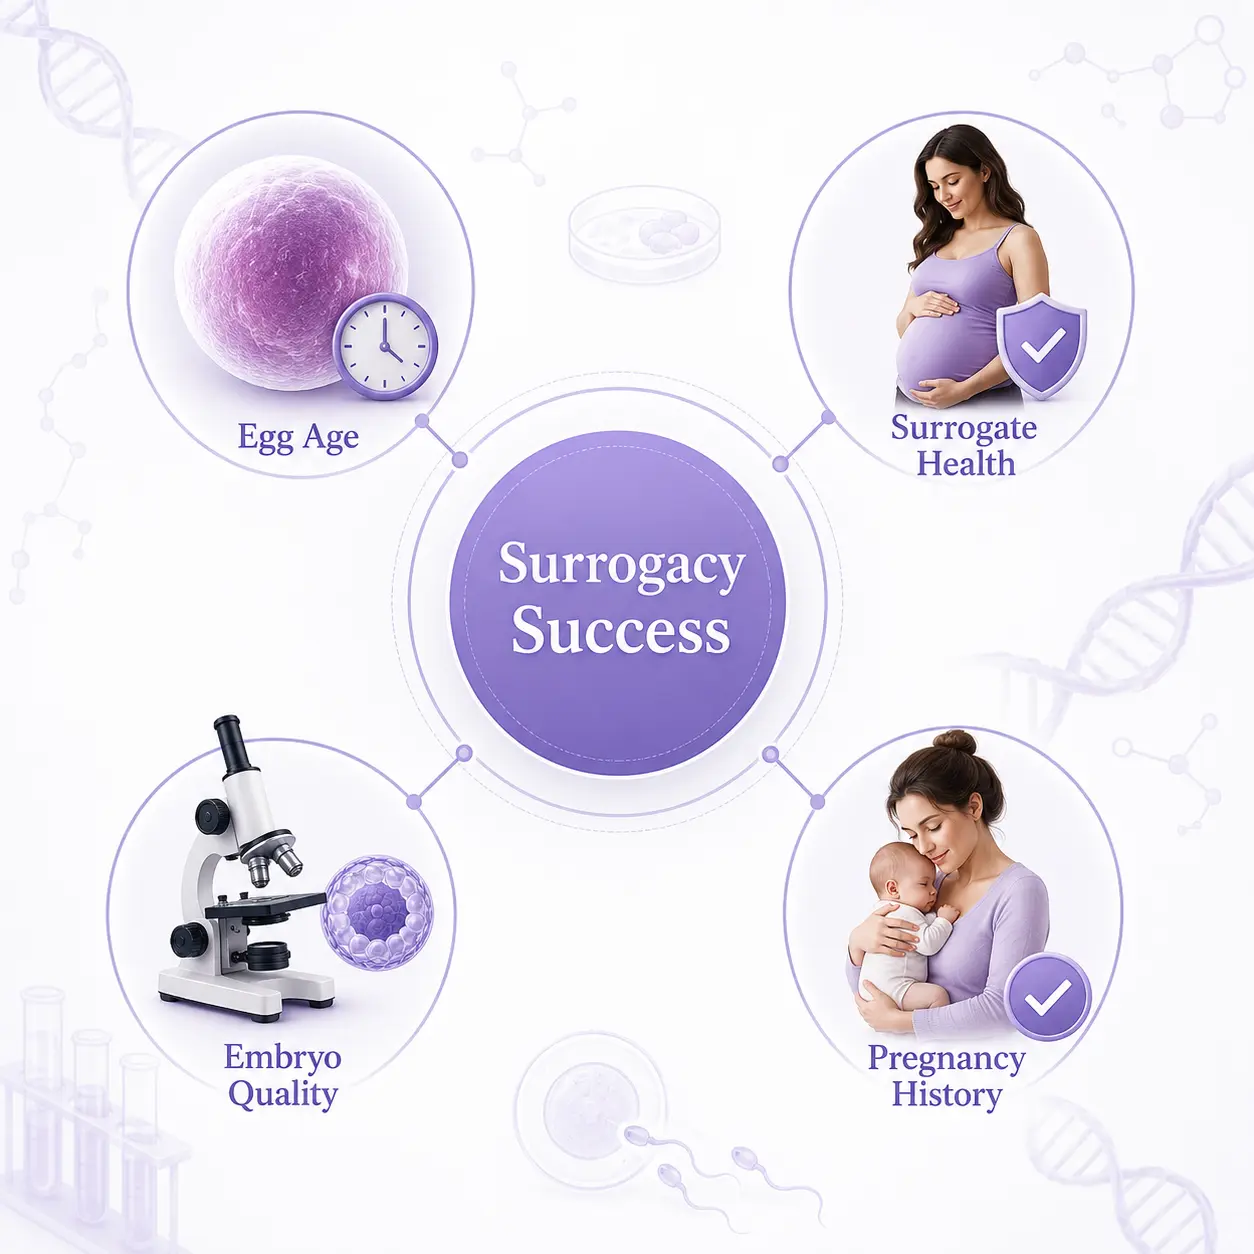
Surrogacy outcomes are shaped by several biological and clinical factors. The most important ones include the egg source, surrogate health, embryo quality, and the medical process surrounding transfer.
Age of the Egg Donor or Intended Mother
Egg quality declines with age, and that decline isn’t gradual — it tends to accelerate in the late 30s and speeds up further after 40. As covered earlier, live birth rates per egg retrieval drop sharply once patients pass their mid-30s, falling to a small fraction of their original rate by the early 40s.
This is exactly why so many surrogacy journeys involving intended mothers over 35 turn to egg donors. When younger donor eggs are used instead, live birth rates per transfer typically climb back up to somewhere between 65% and 70% — and that can rise even higher with additional genetic screening, which we’ll get to below.
Surrogate's Health & Medical History
A surrogate’s overall physical health plays just as large a role as the embryo she’s carrying. Clinics and agencies typically screen for a specific set of markers before approving a candidate, including:
- A healthy BMI range
- No chronic conditions like diabetes, hypertension, or heart disease
- A normal, structurally healthy uterus with no history of complications
- Negative screening for infectious diseases
- Clearance from a psychological evaluation
These aren’t arbitrary checkboxes. A surrogate with an untested or compromised uterine environment faces a meaningfully higher risk of implantation failure or pregnancy complications, regardless of how strong the embryo is. That’s why reputable agencies often reject the majority of applicants who come forward — screening this rigorously is what keeps outcomes consistent.
Embryo Quality & Genetic Testing (PGS/PGD)
The embryo itself is the other half of the equation. Embryos are generally graded on their cell structure and development stage before transfer, and higher-graded embryos implant more reliably.
Genetic testing has become one of the more meaningful advances here. Preimplantation genetic testing for aneuploidy (PGT-A, sometimes still referred to as PGS) screens embryos for chromosomal abnormalities before transfer, allowing clinics to select only embryos with a normal chromosome count. When this testing is added, live birth rates per transfer can climb from the 65–70% range up to 75–80%.
Preimplantation genetic diagnosis (PGD) serves a related but distinct purpose — it’s typically used when intended parents carry a known inherited genetic condition, screening embryos specifically for that condition rather than general chromosomal health.
Surrogate's Previous Pregnancy History
Most agencies require a surrogate mother to have already carried at least one healthy pregnancy to term. That requirement isn’t just about experience — it’s a proven data point. A surrogate whose body has already demonstrated it can sustain a full-term pregnancy without complications is a lower-risk candidate than one with no such history.
A history of pregnancy loss, premature delivery, or complications like preeclampsia, on the other hand, can lower the odds of success for a future pregnancy — which is why detailed obstetric history is one of the very first things a screening process looks at, often before a candidate’s medical testing even begins.
What Should You Ask a Clinic About Its Surrogacy Success Rate?
There is no single standardized success rate for the top surrogacy agencies, fertility clinics, or international surrogacy programs. Most comparable outcome data comes from fertility clinics and national ART reporting systems, while agencies and surrogacy centers may report outcomes using different definitions.
For IVF surrogacy success rates, ask whether the percentage refers to a clinical pregnancy, live birth, embryo transfer, or complete IVF cycle. Also ask how many cases are included, what period the data covers, and whether donor eggs and intended-mother eggs are reported separately.
When comparing family building services and surrogacy programs internationally, these details matter because a higher percentage may simply reflect a different stage of treatment or a different patient group.
Before using a clinic’s number to compare providers, ask:
- Is this pregnancy rate or live birth rate?
- Is it calculated per embryo transfer or per IVF cycle?
- Does the figure include donor eggs and intended-mother eggs separately?
- How many transfers or cases does the percentage represent?
- What time period does the data cover?
If a clinic or surrogacy center gives you a headline number such as “95% success” without defining it, the percentage alone is not enough to understand its outcomes.
Can a Surrogacy Clinic Really Have a 95% Success Rate?
Yes, a clinic can report a 95% surrogacy success rate, but that does not necessarily mean that 95 out of 100 embryo transfers result in a live birth.
A figure this high may refer to pregnancies that have already been clinically confirmed rather than success from the first embryo transfer. A 95% rate after pregnancy confirmation therefore should not be compared directly with a live birth rate per embryo transfer.
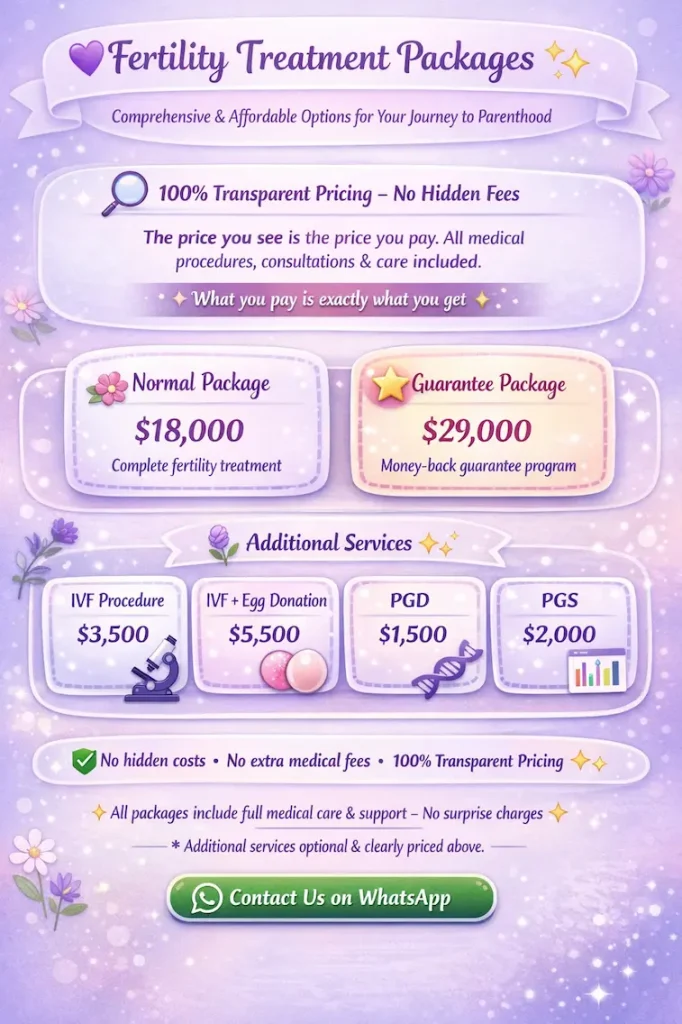
For intended parents considering surrogacy in Iran, a Guaranteed Surrogacy Package may offer a different approach. Depending on the program terms, it can include unlimited IVF cycles and embryo transfers until a live birth is achieved.
This is not the same as claiming a 100% success rate for every transfer. The guarantee provides continued treatment until the agreed outcome is reached, subject to the package terms.
What Lowers Surrogacy Success Rates?
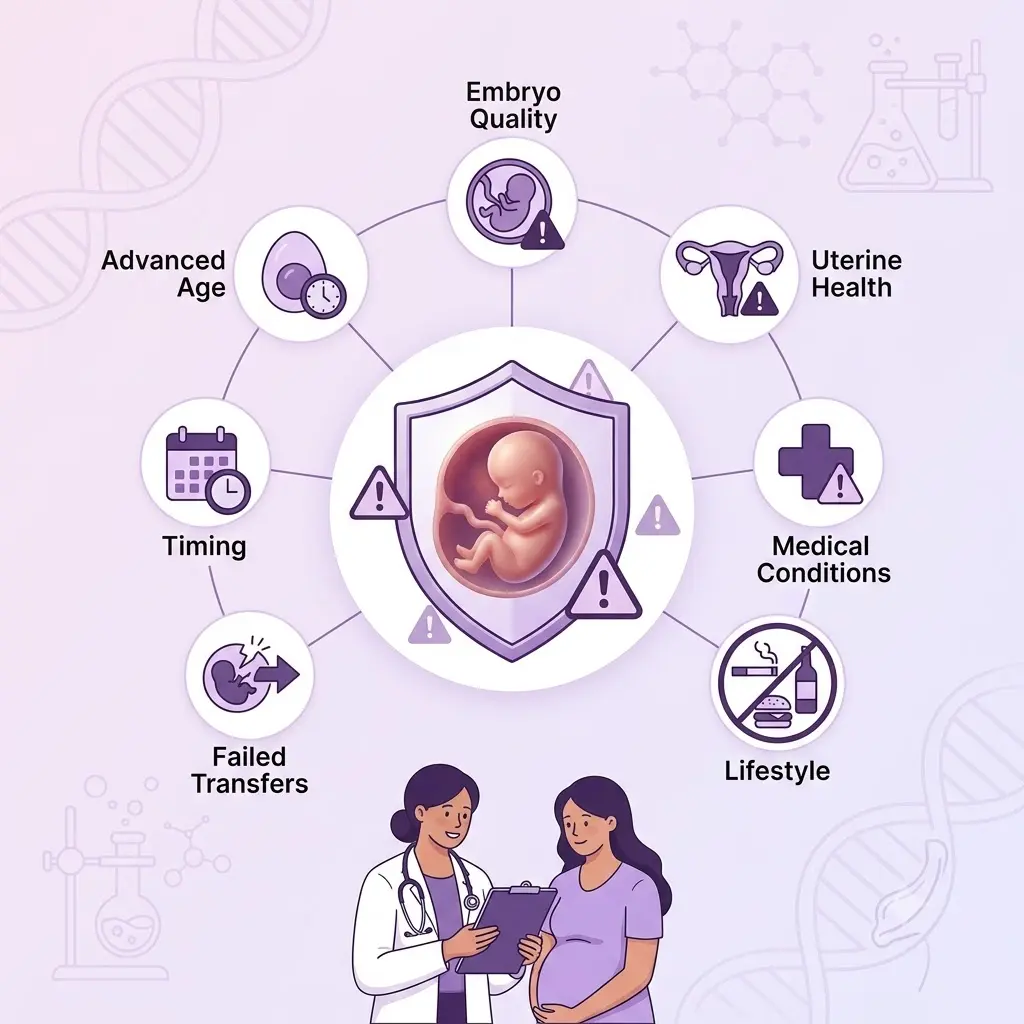
Just as certain factors improve the odds of a successful surrogacy journey, others can quietly work against it. Recognizing these risk factors early — often before treatment even begins — is one of the most effective ways to avoid a failed transfer or pregnancy loss.
Some of the most common factors linked to lower success rates include:
- Advanced egg donor or intended mother age. As covered above, egg quality drops sharply after the mid-30s, and this remains one of the single biggest predictors of a lower success rate.
- Poor embryo quality or untested embryos. Embryos with chromosomal abnormalities are far more likely to fail to implant or end in early miscarriage, particularly when genetic testing hasn’t been used to screen them beforehand.
- Uterine abnormalities in the surrogate. Conditions like fibroids, scarring, or a thin uterine lining can prevent an otherwise healthy embryo from implanting successfully.
- Underlying health conditions. Poorly managed diabetes, thyroid disorders, autoimmune conditions, or high blood pressure can all interfere with implantation or increase pregnancy complications.
- Lifestyle factors. Smoking, alcohol use, poor nutrition, and high stress levels have all been linked to lower implantation and pregnancy rates.
- Repeated implantation failure. A surrogate who has experienced multiple failed transfers in the past — for herself or in a prior surrogacy journey — faces statistically lower odds on future attempts, even with a high-quality embryo.
- Timing and coordination issues. Even a healthy embryo can fail to implant if the transfer isn’t precisely timed to the surrogate’s cycle and uterine lining readiness.
It’s worth noting that a single failed attempt doesn’t mean surrogacy “didn’t work” for good. Many of these factors — like uterine conditions or timing — can be identified and corrected before a second transfer, which is why thorough screening and monitoring matter just as much before treatment as during it. Clinic experience plays a role here too, which we cover in more detail below.
How to Improve Your Chances of Surrogacy Success
While no clinic or agency can guarantee a specific outcome, there are concrete steps that meaningfully shift the odds in your favor. Rather than repeating the factors already covered, here’s how to actually act on them:
- Request genetic testing as a standard step, not an add-on. If your clinic doesn’t proactively offer PGT-A/PGS screening, ask why — it’s one of the most well-documented ways to reduce failed transfers.
- Discuss donor eggs early if maternal age is a factor, rather than after a first attempt doesn’t succeed. Bringing it up upfront can save a full cycle of time.
- Ask to see the surrogate’s full screening file, not just a summary — pregnancy history, BMI, and medical clearance should all be transparent and verifiable.
- Confirm a monitoring plan is in place, not just for the transfer itself, but for the weeks before it — uterine lining and cycle timing should be tracked, not assumed.
- Set expectations for more than one attempt. Going in mentally prepared for two or three transfers, rather than expecting success on the first, tends to reduce stress and decision fatigue if a first attempt doesn’t work.
The common thread across all of these: the more specific and verifiable the information you ask for, the more control you actually have over the outcome — even though no single step guarantees it.

Why Do Surrogacy Success Rates Differ Between Clinics?
If you’ve spent any time comparing agencies or fertility clinics, you’ve likely noticed something confusing: reported success rates can vary widely — sometimes by 20 percentage points or more — even between clinics offering what looks like the same service. That gap isn’t random. It usually comes down to a few structural differences in how a clinic operates, not just luck.
The CDC itself acknowledges this variability in its own guidance on interpreting ART data, noting that clinics performing fewer cycles tend to show more year-to-year fluctuation in their reported outcomes, while high-volume clinics tend to post more stable, consistent numbers over time.
Surrogate Screening Standards
How selective a clinic or agency is about accepting surrogate candidates has a direct, measurable impact on outcomes. Some programs accept a wide range of applicants with minimal screening; others reject the overwhelming majority of candidates who apply, accepting only those who meet strict medical, psychological, and lifestyle criteria.
A program that only approves candidates with a proven full-term pregnancy history, a healthy BMI, no chronic conditions, and a structurally normal uterus is, by definition, starting every journey with a lower-risk profile than one with looser standards. That difference alone can account for a meaningful gap in reported success rates between two otherwise similar-looking programs.
IVF Laboratory Quality & Medical Team Experience
The technical side of the process matters just as much as who’s carrying the pregnancy. Embryo development, grading, and the transfer procedure itself are all highly sensitive to lab conditions and operator experience — small differences in embryo handling or transfer timing can affect implantation rates in ways that aren’t always obvious from the outside.
Clinics with more experienced reproductive endocrinologists, higher cycle volumes, and modern lab equipment (including access to genetic testing like PGS/PGD) tend to post more consistent outcomes over time. This is also part of why the CDC cautions patients against comparing clinic success rates without context — a clinic serving a higher proportion of complex or older-age cases may report lower raw numbers than one serving a younger, lower-risk patient population, even if its actual clinical skill is comparable or better.
Surrogacy Success Rates in Iran
That same logic — screening standards, lab quality, and clinical experience — is exactly what explains why surrogacy in Iran has become one of the more closely watched options for international intended parents in recent years, alongside its well-known cost advantages.
Why Iran Achieves High Success Rates
Iran has offered a legally recognized framework for surrogacy since 2003, giving fertility clinics there decades to refine both the medical and legal sides of the process. That legal stability matters clinically too — it means clinics can operate with clear government oversight and standardized protocols, rather than working around legal gray areas that can complicate care in less regulated destinations.
On the medical side, several Iranian fertility centers have invested heavily in the same technologies driving outcomes elsewhere: advanced IVF laboratories, embryo grading, and genetic testing options like PGS and PGD — the same technology behind gender selection in Iran, which has become an increasingly requested option among international intended parents.
Combined with rigorous surrogate screening — a practice that, as covered earlier, has a direct impact on outcomes — this is part of why success rates reported by leading Iranian clinics are often comparable to, or higher than, rates reported in the U.S. and parts of Europe.
For families specifically interested in gender selection, this same genetic testing infrastructure is what makes accurate, medically reliable results possible.
How VitaLife Maintains a 95% Success Rate
At VitaLife, this same approach shapes how every journey is structured. The clinic reports a surrogacy success rate of over 95% once pregnancy is confirmed, a figure built on a few consistent practices:
- Selective surrogate screening. Only about 1 in 10 applicants is approved, based on strict medical, psychological, and lifestyle criteria — including a proven pregnancy history, healthy BMI range, and no chronic health conditions.
- Comprehensive pre-transfer evaluation. Every surrogate undergoes full medical and physical assessments before an embryo transfer is scheduled, reducing the chance of an unexpected complication mid-process.
- An experienced medical team. More than 50 medical professionals, with a combined 200+ years of experience in reproductive medicine, oversee the clinical side of each journey.
- Access to genetic testing. Intended parents can add PGS or PGD screening to their package, which — consistent with the broader research on embryo testing — has been associated with improved outcomes and reduced miscarriage risk.
IVF vs. Surrogacy Success Rates
A common question behind IVF surrogacy success rates is why outcomes can look different when the same IVF technology is used. The embryo creation process is similar, but the person carrying the pregnancy is different, which can affect outcomes.
As covered earlier, when an intended mother carries her own IVF pregnancy, live birth rates decline steeply with age, per the CDC’s National ART Surveillance System.
When a gestational carrier is used instead, those numbers shift upward — even using the exact same egg source. Research on gestational surrogacy outcomes, published through the American Society for Reproductive Medicine, shows gestational carriers using the intended mother’s own eggs achieve a clinical pregnancy about 51.8% of the time, compared to 44.7% for non-gestational-carrier IVF cycles using the same egg type. The gap holds with donor eggs too: about 69.8% for gestational carriers versus 65.0% for non-carrier cycles.
That 5–7 percentage point difference isn’t about better embryos — it’s about the uterine environment they’re being placed into. Gestational carriers are typically pre-screened for a proven pregnancy history and a healthy, complication-free uterus, which is exactly the kind of environment that supports implantation more reliably than one with unknown or higher-risk factors.
In practical terms, this means:
- IVF success rates reflect the combined effect of egg quality and the uterus carrying the pregnancy — two variables working together, for better or worse.
- Surrogacy success rates isolate one of those variables. By using a surrogate with a track record of healthy, full-term pregnancies, much of the uterine-related uncertainty is already accounted for before the embryo is even created.

Is the First Embryo Transfer Always Successful?
Short answer: no — and that’s completely normal. A single embryo transfer succeeding on the very first try is common, but it’s far from guaranteed, even with a high-quality embryo and an experienced surrogate.
Per-transfer success rates typically fall somewhere between 20% and 50%, depending heavily on age, embryo quality, and whether the embryo was tested for chromosomal normalcy beforehand. That range explains why many intended parents and surrogates go into a first transfer hopeful, but prepared for the possibility that it may not be the one that results in a pregnancy.
What matters more than any single attempt is the cumulative success rate — the likelihood of achieving a live birth across multiple transfers or cycles, not just one. A large UK study published in Human Reproduction found a cumulative live birth rate of about 42% after three complete IVF cycles.
A first transfer that does not result in pregnancy therefore does not determine the outcome of the entire treatment journey.
A few things commonly explain why a first transfer doesn’t succeed:
- Embryo-uterine timing. Even a healthy embryo needs to be placed at precisely the right point in the surrogate’s cycle.
- Undetected uterine factors. Conditions like a thin lining or minor implantation issues aren’t always apparent until after a transfer is attempted.
- Embryo quality. Not every embryo — even a good one on paper — is chromosomally normal, which is part of why many clinics now recommend PGT-A testing before transfer.
Some of these factors can be identified and addressed before a subsequent transfer, which is why monitoring and follow-up matter after an unsuccessful attempt.
What is the average Surrogacy Success Rate?
Most gestational surrogacy journeys report a success rate somewhere between 70% and 95%, depending on how the number is measured. Live birth rates per embryo transfer typically fall in the 65–80% range, while rates measured after a pregnancy is already confirmed often climb above 90%. The wide range is normal — it reflects differences in age, embryo quality, and whether genetic testing was used, not inconsistency in the process itself.
Does age affect surrogacy success rates?
Yes, though it's the egg source's age that matters most, not the surrogate's. Egg quality declines significantly after the mid-30s, with live birth rates dropping from around 43% under age 35 to under 5% after 42. Using a younger surrogate doesn't offset older egg quality — which is why donor eggs are often recommended for intended mothers over 35 or 40.
Does PGS/PGD improve success rates?
Yes. Genetic testing (PGT-A, sometimes called PGS) screens embryos for chromosomal abnormalities before transfer, which can raise live birth rates per transfer from roughly 65–70% up to 75–80%. PGD serves a different purpose — it screens for a specific inherited condition when intended parents are known carriers — but both forms of testing help clinics select the healthiest embryo available before transfer.
Is gestational surrogacy more successful than traditional?
Generally, yes. Gestational surrogacy accounts for the vast majority of arrangements today and benefits from IVF's precision, embryo selection, and surrogate screening standards. Traditional surrogacy, by contrast, is rarely offered by modern clinics, and reliable success rate data for it is limited — partly because so few programs still perform it.
What is the surrogacy success rate in Iran?
Leading fertility centers in Iran, including VitaLife, report surrogacy success rates above 95% once a pregnancy is confirmed. This is supported by Iran's legally regulated surrogacy framework (in place since 2003), access to advanced IVF technology, and strict surrogate screening standards.
Can surrogacy succeed after a failed embryo transfer?
Yes, and it often does. A single failed transfer doesn't reflect a failed process — it's frequently due to timing, uterine lining, or embryo-specific factors that can be identified and adjusted for the next attempt. Research shows that the large majority of successful live births occur within the first three transfer attempts, so a second or third try remains genuinely promising for most patients.
Surrogacy success rates are meaningful only when you know what the percentage measures. Pregnancy, clinical pregnancy, live birth, embryo transfer, and IVF cycle rates describe different stages of the journey.
For intended parents comparing clinics or programs, the most useful approach is to look beyond the headline number and ask how it was calculated, how many cases it represents, and which patient group it covers.